
Health System Relies More on Migrant Workers Despite Visa Barriers and Exploitation: Nursing Bodies
 Rex WiderstromUpdated 11 hours Ago3 Mins read
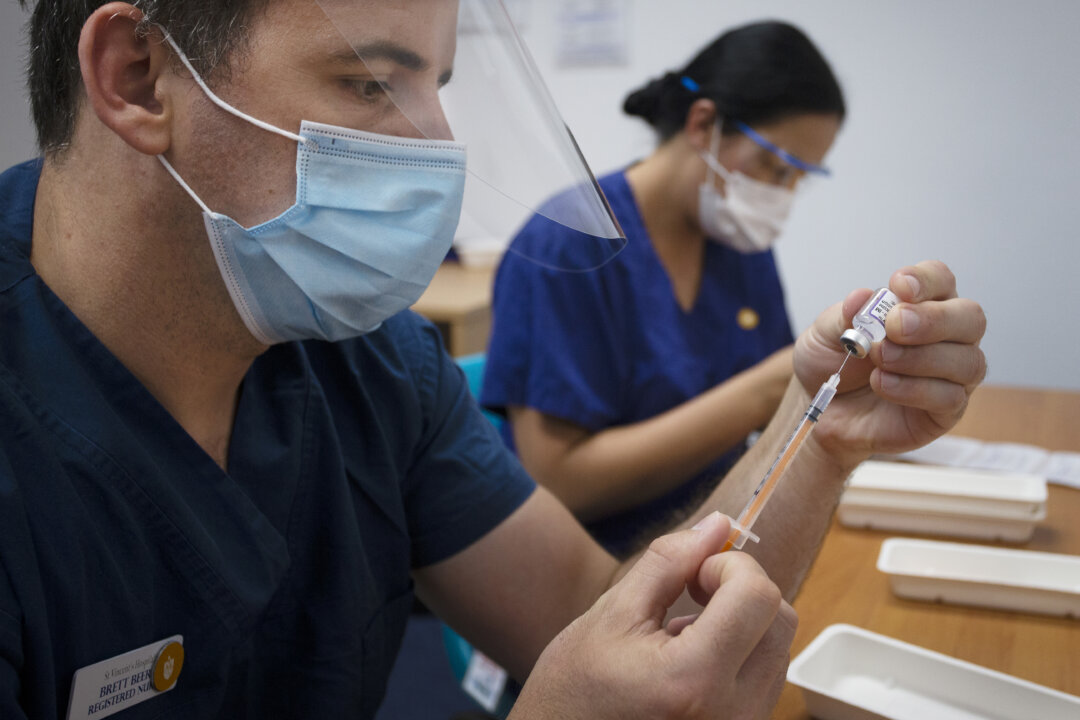
Australia’s health and aged care systems are becoming increasingly reliant on migrant workers even as visa barriers, registration bottlenecks and workplace exploitation hinder their entry and retention, three peak nursing and midwifery bodies have told a parliamentary inquiry.
Appearing separately before the Joint Standing Committee on Migration’s inquiry into the value of skilled migration, Australian Nursing and Midwifery Federation (ANMF) federal secretary Annie Butler said around 40 percent of the sector’s workforce was born overseas, while 20 percent was educated in another country.
“It’s a really significant a number and a significant contribution that those people make to not just to our workforces, but to our health and aged care systems and to the well-being of our communities,” she told the Committee.
Despite the contribution of migrant workers, the peak bodies said labour shortages remain a significant challenge for the healthcare industry.
The Australian Nursing and Midwifery Accreditation Council (ANMAC), the government’s approved assessing authority, said in its submission (pdf) almost 28,000 internationally qualified nurses had registered in the past two years alone.
Yet the workforce is growing at just 2.2 percent annually, below the 3.6 percent growth rate needed to meet demand.
Kathryn Zeitz, CEO of the Australian College of Nursing (ACN), told the Committee current projections show “a shortfall of 32,000 nurses currently, rising to almost 80,000 nurses by 2035.”
Butler argued that retention, rather than supply, is the “number one issue.” She said thousands of registered nurses remain outside the workforce and cited Victoria’s mandated nurse-to-patient ratios as an example, saying more than 10,000 nurses returned to the system after the ratios were introduced.
Migration Rules Worsen Labour Shortages
At the same time, the witnesses said gaps in migration rules were worsening labour shortages by making it harder to recruit migrant workers.
Kathryn Baird, ANMAC’s director of skilled migration services, said internationally qualified nurses who need to sit Australia’s clinical exam for registration have no dedicated visa to enter the country and must instead apply for what is essentially a holiday visa.
The exam itself costs around $4,000 (US$2,900), and if the applicant fails they have to pay the same amount to re-sit.
Zeitz separately flagged a “bureaucratic rule” requiring nurses who qualified before 2017 to sit an additional clinical exam regardless of experience, calling it a barrier to recruiting senior nurses into leadership and academic roles.
Baird said ANMAC’s own skills-assessment process is not the bottleneck: applications have roughly doubled since the pandemic to about 16,000 a year, fewer than 1 percent are rejected, and turnaround is five to seven days once the four-week waitlist clears.
However, the registration pathway that follows, run by other bodies, “can be upwards of seven to nine months on average,” she said.
Both ACN and ANMAC also called for the 45-year age cap on skilled visa points to be lifted.
“When they hit that birthday, one day their age is worth 10 points, and the next day it’s worth zero,” Baird said, arguing that this does not align with national policies on employment, pensions and social security, given Australians can work until 67.
Exploitation and Housing Issues
The ANMF’s written submission (pdf) outlined more severe exploitation of migrant workers in the sector, including a contract that required visa holders to pay $50 for every day they did not work during a five-year term if they resigned early, potentially leaving them with debts of up to $90,000.
It also cited cases of Pacific Australia Labour Mobility scheme workers being used as “super-carers,” performing nursing duties while receiving only the wage of an aged care worker.
Housing also emerged as a persistent barrier for migrant workers.
Baird told the Committee that some nursing students were camping in cars and caravan parks to complete rural clinical placements.
“There are challenges in in getting people to stay in remote locations where they may not have access to their cultural communities and those sorts of things,” she said.
“So we do see people going out to rural and remote locations for visa conditions and those sorts of things, but then very quickly coming back into metropolitan locations once those visa conditions become removed, so it is [a] retention [issue] for those in those communities as well.”
All three organisations backed streamlined, ethically recruited skilled migration alongside greater domestic investment—including an independent national workforce planning body and a national nursing workforce strategy—rather than relying on migration to substitute for fixes to local training and retention.






Chinese Entrepreneur Who Spent 26 Years Petitioning the Regime Escapes to Germany
A Chinese entrepreneur who says the regime seized hundreds of thousands of...

Several Injured in Knife Attack in Guangzhou University District
A knife attack at the GOGO New World commercial complex in the...

Palau’s President Says US Security Partnership Is Essential as China Pressures Island Nation
KOROR, Palau—When Surangel Whipps Jr. was pursuing an MBA at UCLA in...

Trump Nominates Republican Congressman Wesley Hunt as Ambassador to Saudi Arabia
Rep. Wesley Hunt (R-Texas) in Trinity, Texas, on Feb. 19, 2026. Madalina...




